
The operating theatre has seen its share of technological advancements, from robotic assistance to advanced imaging. But the fundamental act of a surgeon looking at the operative field has remained largely unchanged. Now, immersive goggles are entering the discussion, overlaying critical patient data directly into the surgeon's line of sight, a concept that could redefine intraoperative decision-making.
These devices aim to integrate real-time diagnostics and anatomical mapping with the physical surgical environment, potentially streamlining complex procedures and reducing cognitive load. The question is whether this technology delivers on its ambitious claims or merely adds another layer of complexity to an already intricate process.
Surgical procedures, particularly those involving intricate anatomy or minimally invasive approaches, demand exceptional spatial awareness and the ability to integrate diverse data streams. Surgeons routinely consult imaging scans, patient charts, and vital signs monitors, often requiring them to shift their gaze away from the operative field. This constant reorientation can introduce micro-pauses and potential for distraction, particularly in time-sensitive situations. The unmet need here is a seamless, integrated display of critical information that does not disrupt the surgical flow.
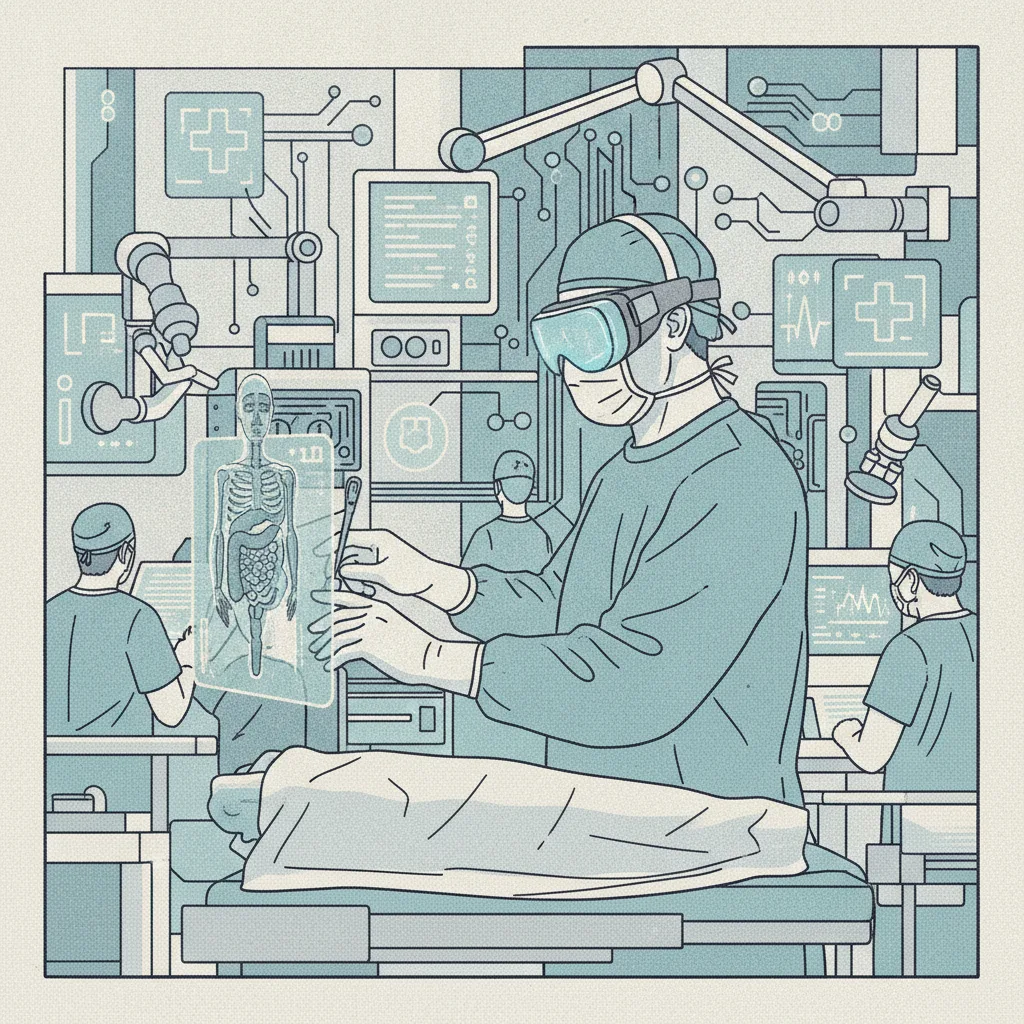
Immersive goggles, often referred to as augmented reality (AR) or mixed reality (MR) headsets, aim to address this by projecting digital information directly onto the surgeon's view of the patient. This technology can display anything from pre-operative CT or MRI scans, highlighting critical structures like tumors or blood vessels, to real-time physiological data. The goal is to create a 'heads-up' display, keeping all relevant information within the surgeon's immediate visual field, thereby reducing the need to look away and re-focus.
The Promise of Enhanced Visualization
The primary benefit touted for immersive goggles is the enhancement of visualization. In complex oncological resections, for instance, a surgeon might use AR to overlay a 3D reconstruction of a tumor, showing its precise boundaries and proximity to vital organs. This can be particularly useful in areas where anatomical landmarks are distorted by disease or previous surgery. The ability to 'see through' tissue to underlying structures offers a new dimension to surgical planning and execution.
Beyond tumor margins, these systems can project vascular networks, nerve pathways, or even the trajectory of surgical instruments in real-time. This capability is especially compelling for minimally invasive procedures, where the surgeon's view is already mediated by a screen. Integrating AR into laparoscopic or robotic platforms could provide a more intuitive and spatially accurate representation of the operative field, potentially shortening learning curves for new techniques. The integration of AI in robotic surgery is already changing how procedures are performed, and AR goggles represent a logical next step in this evolution.
The technology also holds the potential for surgical education and training, as novice surgeons could wear these goggles to observe a procedure, with the system highlighting key anatomical points or demonstrating correct instrument placement. This 'guided' learning environment offers a more interactive and immersive experience than traditional video recordings or cadaveric dissection. It allows for repeated practice in a simulated but visually rich environment, fostering skill acquisition before entering the operating room.
But the practical application of these systems in live surgery presents challenges. Calibration accuracy is paramount; any misalignment between the projected image and the actual anatomy could lead to catastrophic errors. The latency of the display, the field of view, and the resolution of the projected images must all be near-perfect to be clinically useful. The ergonomics of wearing a headset for extended periods during surgery, often in sterile environments, needs careful consideration to avoid surgeon fatigue or contamination risks.
Integrating Data and Improving Precision
Immersive goggles are not just about seeing more; they are about seeing smarter. The ability to integrate real-time physiological data, such as heart rate, blood pressure, or oxygen saturation, directly into the surgeon's view could provide immediate context for patient responses during surgery. Imagine a surgeon performing a delicate cardiac procedure, with the patient's ECG trace and real-time cardiac output displayed unobtrusively in their peripheral vision. This immediate access to critical metrics could facilitate quicker responses to adverse events.
Precision is another area where these goggles aim to make a difference. In orthopaedic surgery, for example, AR can guide the precise placement of screws or prosthetics, ensuring optimal alignment and fit. For neurosurgery, the overlay of functional brain mapping data can help surgeons navigate complex neural pathways while avoiding critical areas. This level of precision, if consistently achievable, could lead to improved patient outcomes and reduced complication rates.
Still, the data integration aspect requires robust and secure interoperability with existing hospital information systems. Ensuring that patient data is accurately transmitted, displayed, and updated in real-time without compromising privacy or system stability is a significant technical hurdle. The regulatory pathway for such devices, which combine medical imaging, real-time data, and surgical guidance, is also complex, requiring rigorous validation of safety and efficacy.
The cost of these advanced systems is another practical consideration. While the long-term benefits in terms of reduced complications or improved efficiency might justify the investment, the initial outlay for hardware, software, and integration can be substantial. This could limit adoption, particularly in healthcare systems with tighter budgets. The real reason AI is reshaping clinical skill acquisition is often tied to these economic and efficiency gains, and AR goggles will face similar scrutiny.
Where the Technology Falls Short (For Now)
Despite the excitement, current immersive goggle technology faces several limitations that prevent widespread adoption. The field of view in many commercial AR headsets remains somewhat restricted, meaning the digital overlay might not cover the entire surgical field, forcing the surgeon to still look away or adjust their head position frequently. This can negate some of the intended benefits of a 'heads-up' display.
The resolution and brightness of the projected images are also critical. In a brightly lit operating room, the digital overlay must be sufficiently clear to be easily discernible without causing eye strain. Early iterations of these devices have sometimes struggled with image clarity and contrast, particularly when overlaid on complex anatomical structures. The weight and bulk of the headsets can be a concern for surgeons during long procedures, impacting comfort and potentially leading to neck fatigue.
But perhaps the most significant challenge is the human factor. Surgeons are highly trained professionals with established routines and preferences. Introducing a new, visually intensive interface requires a significant adaptation period. The cognitive load associated with processing both the physical environment and the overlaid digital information simultaneously can be considerable. While the aim is to reduce distraction, a poorly designed interface could inadvertently increase it. The Oxford Handbook of Clinical Medicine emphasizes the importance of clear, unambiguous information in high-stakes environments, a principle that applies directly to AR in surgery.
The current evidence base for improved patient outcomes directly attributable to immersive goggles is still nascent. While feasibility studies and case reports demonstrate technical success and surgeon satisfaction, large-scale randomized trials comparing AR-assisted surgery to conventional methods, particularly on hard endpoints like complication rates, operative time, or patient recovery, are largely absent. Without this robust evidence, widespread clinical adoption will remain cautious.
Immersive goggles represent a fascinating, if still largely unproven, frontier in surgical technology. The concept of overlaying critical data directly into the surgeon's field of view is compelling, as it promises to enhance precision and reduce cognitive load. But the transition from proof-of-concept to routine clinical practice is fraught with technical and human challenges.
Clinicians should view these developments with a healthy dose of skepticism tempered by curiosity. While the potential for improved visualization in complex cases and enhanced training is clear, the current generation of devices needs to demonstrate consistent accuracy, ergonomic comfort, and, a measurable improvement in patient outcomes. Without robust data (n=unknown, CI=unknown) from well-designed trials, these goggles risk becoming an expensive novelty rather than an indispensable tool.
The industry faces the task of refining the technology to overcome limitations in field of view, resolution, and latency, while simultaneously ensuring seamless integration with existing hospital infrastructure. Regulatory bodies will need to establish clear pathways for devices that blend imaging, data, and surgical guidance, demanding rigorous validation. For now, the best approach for surgeons is to observe, evaluate, and demand evidence before embracing the next shiny object in the operating room.
- The Pivot Immersive goggles are moving beyond conceptual stages, offering real-time data overlay in surgical fields.
- The Data Early applications focus on enhanced visualization and improved spatial understanding during procedures.
- The Action Clinicians should monitor developments in augmented reality for surgical training and complex case planning.
ART-2026-1883
·10/26
Drafted with AI assistance, reviewed and approved by the editorial team. This publication is intended for healthcare professionals, researchers, and life science industry professionals. Content is provided for informational and educational purposes only and does not constitute medical advice.

Digital health and patient experience are my beat: the apps, the wearables, the real-world evidence claims, and whether any of it changes outcomes. Sceptical by training and optimistic by instinct.
Cite This Article
Ward S, Voss M. Surgical goggles: are we trading focus for more data?. The Life Science Feed. Published October 7, 2026. Updated October 7, 2026. Accessed October 7, 2026. https://thelifesciencefeed.com/healthcare-sys-and-biz/ai-in-healthcare/innovation/surgical-goggles-are-we-trading-focus-for-more-data.
Editorial & AI Standards
All content is researched from peer-reviewed, open-access sources: published trial data, clinical guidelines, and regulatory filings. AI tools are used solely to structure and summarise that evidence; no AI-generated conclusions appear without editor verification against the primary source.
Every article is reviewed by a named editor before publication. Source citations are listed in the References section. This content does not represent the views of any pharmaceutical company, medical device manufacturer, or healthcare provider.
Licence & Rights
© 2026 The Life Science Feed. All rights reserved. Unless otherwise indicated, all content is the property of The Life Science Feed and may not be reproduced, distributed, or transmitted in any form or by any means without prior written permission.
Medical Disclaimer
The information provided on The Life Science Feed is for educational and informational purposes only. It is not intended as a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified healthcare provider regarding any medical condition or treatment decision. Never disregard professional medical advice or delay in seeking it because of something you have read on this website.
References
1. Polverino E, Goeminne PC, McDonnell MJ, et al. European Respiratory Society guidelines for the management of adult bronchiectasis. Eur Respir J. 2017;50(3). doi:10.1183/13993003.00629-2017
2. Batchelor TJP, Rasburn NJ, Abdelnour-Berchtold E, et al. Guidelines for enhanced recovery after lung surgery: recommendations of the Enhanced Recovery After Surgery (ERAS®) Society and the European Society of Thoracic Surgeons (ESTS). Eur J Cardiothorac Surg. 2019;55(1):91-115. doi:10.1093/ejcts/ezy301
3. Avila G, Galindo-Moreno P, Soehren S, Misch CE, Morelli T, Wang HL. A novel decision-making process for tooth retention or extraction. J Periodontol. 2009;80(3):476-91. doi:10.1902/jop.2009.080454
4. McIsaac DI, Gill M, Boland L, et al. Prehabilitation in adult patients undergoing surgery: an umbrella review of systematic reviews. Br J Anaesth. 2022;128(2):244-257. doi:10.1016/j.bja.2021.11.014
5. Hopwood S, Khan F, Kemp J, Rehm A, Ashby E. Clubfoot: an overview and the latest UK guidelines. Br J Hosp Med (Lond). 2023;84(1):1-7. doi:10.12968/hmed.2022.0380
6. Saugel B, Buhre W, Chew MS, et al. Intra-operative haemodynamic monitoring and management of adults having noncardiac surgery: A statement from the European Society of Anaesthesiology and Intensive Care. Eur J Anaesthesiol. 2025;42(6):543-556. doi:10.1097/EJA.0000000000002174